TL;DR
Panic attacks are far more common than panic disorder. Up to 28% of adults experience one in their lifetime, while only about 4.7% develop panic disorder. The key distinction lies not in the attacks themselves but in the time between them. Panic disorder requires at least one unexpected, uncued panic attack plus either persistent worry about future attacks or significant avoidance behavior aimed at preventing them. Panic attacks that occur outside of panic disorder are typically linked to other conditions like depression, PTSD, or social anxiety, and often signal greater overall symptom severity. Understanding which category you fall into matters for treatment. Therapy for panic disorder uses CBT and exposure-based techniques to help people move beyond coping and start living without letting fear and avoidance dictate their choices.
Panic Attacks vs. Panic Disorder: Why Does the Distinction Matter?

Anxiety is a complicated and uncomfortable thing. Anxiety symptoms are more ushy gushy than our current diagnostic system would suggest. Sometimes people have symptoms that seem to fit with a few different diagnoses, or don’t meet full criteria for a particular diagnosis, but the level of severity of symptoms suggests that they do have a mental illness. That being said, the DSM-5 (Diagnostic and Statistical Manual of Mental Disorders, 5th Edition) does recognize that panic attacks can occur outside of the context of panic disorder. It is a known phenomenon in the research and clinical worlds.
More people experience panic attacks than have panic disorder. It is estimated that about 13-28% of adults have had a panic attack at least once in their lives (Jonge et al., 2017; Kessler et al., 2006), so experiencing a panic attack is common. However, only about 4.7% of adults have panic disorder at some point in their lives (NIMH). In this blog, I’ll discuss what it can look like to have a panic attack without having panic disorder, and what the difference is between those who have panic attacks only and those who have panic disorder.
Panic Attacks in Different Contexts
Panic attacks are sudden, intense surges of fear that come to their peak within seconds or a few minutes. They can happen even in people who don’t have panic disorder. Panic attacks that happen in the context of folks who do not have panic disorder are associated with higher severity of symptoms. They’ve been associated with higher severity in major depressive disorder (what we typically mean when we talk about depression), social anxiety disorder, posttraumatic stress disorder (PTSD), and schizophrenia (Wideburg et al., 2024). In other words, having panic attacks (outside of panic disorder) is an indication that your mental illness may be more severe and more impairing.
Panic attacks (without panic disorder) are still more common within anxiety disorders (including separation anxiety disorder, generalized anxiety disorder, specific phobia, and social anxiety disorder), depressive disorders (including MDD and persistent depressive disorder), and PTSD. They can also occur in OCD and psychosis. Most of the time, however, most people who regularly struggle with panic attacks have panic disorder. This is seen in the data. Panic attacks tend to happen repeatedly over longer periods of time for those with panic disorder than those without it (Kessler et al., 2006). In contrast, people who have panic attacks but do not have panic disorder tend to experience them for fewer years on average.
If generalized worry or fear of judgment in social situations is a concern, online therapy for generalized and social anxiety may help.
Panic Disorder, Beyond Panic Attacks
If having panic attacks doesn’t necessarily mean you have panic disorder, then what are the other aspects of panic disorder? The other requirements for being diagnosed with panic disorder are as follows: More than one of the panic attacks must be unexpected, or uncued; there is either persistent worry about having another panic attack or significant avoidance of situations or behaviors that are feared will bring on panic attacks.
Cued vs. Uncued Panic Attacks
For someone to have panic disorder, more than one of their panic attacks has to have come “out of the blue.” To be specific, the panic attack must arise from an otherwise calm state or while emerging from sleep (like in nocturnal panic attacks). Uncued panic attacks have no obvious cue or trigger. For example, if you were simply getting groceries at the store, with nothing that would cause any anxiety for you happening, and all of a sudden, you had a panic attack, that would be uncued.
Cued panic attacks happen when there is some kind of a trigger for anxiety or fear. For example, if someone with PTSD encounters a loud sound and gets a sudden rush of anxiety that leads into a panic attack, that would be cued.
Persistent Worry or Significant Avoidance

The other building block of panic disorder involves what happens between panic attacks. For those without panic disorder, a panic attack may be unpleasant and take some time to physically recover from. However, folks with panic disorder must either experience a lot of worry and concern about having another panic attack, or engage in significant avoidance with the goal of avoiding another panic attack (or both).
Folks with panic disorder may spend much of their time concerned about either having a panic attack or about the feared consequences of having one. These consequences, although inaccurate, are severe and may include having a heart attack, fainting, dying, or “going crazy.” These are common fears I see at Leap Counseling associated with panic disorder. It is these worries about the dangerousness of panic attacks that set them apart.
Avoidance can become extreme, even to the point of developing agoraphobia and never leaving the home. It can also be less extreme but still significant enough that it gets in the way of doing the things a person wants to do. The goal of the avoidance behaviors is to prevent a panic attack from happening. Folks will often avoid activities that increase physiological arousal (like drinking coffee or exercising); situations where they have had a panic attack before or where it would be difficult to escape or get help if a panic attack did occur (such as a crowded mall or the middle of a lecture hall).
People with panic disorder also often carry around “safety signals,” items or people that make them feel more safe when going places that feel less safe. These often include water bottles, snacks, a close loved one, a cell phone, and even emergency phone numbers.
There is Hope: Treatment of Panic
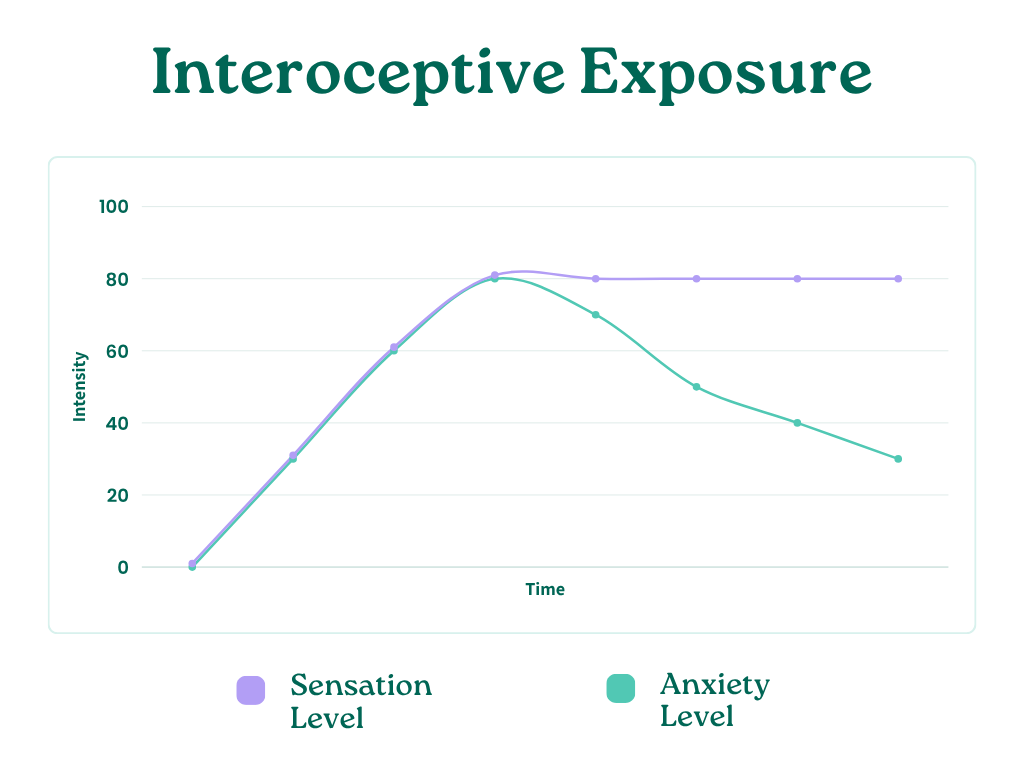
The most effective treatment for panic disorder is cognitive-behavioral therapy (CBT) tailored for panic disorder. The cornerstone of CBT for panic is exposure therapy. This treatment involves intentionally exposing oneself to one’s triggers, without the use of safety signals or any other behaviors whose purpose is to feel safer. This means feeling your anxiety fully, but it allows your body to learn something new.
What we find is that, by learning to tolerate and accept anxiety, we experience less of it over time. It has been shown to be extremely effective for panic disorder. It is done with the support of a therapist, who serves as your cheerleader, educator, and guide through the process. While scary, CBT for panic allows people to stop just coping with panic and start living. As an online panic disorder therapist, I find that people are more courageous than they think!

Keep Learning
Explore blogs on similar topics: